
Treatments
Spinal Injections
X-ray-guided injections that help find the source of back and neck pain — and calm it so you can move and recover.
Overview
Understanding spinal injections
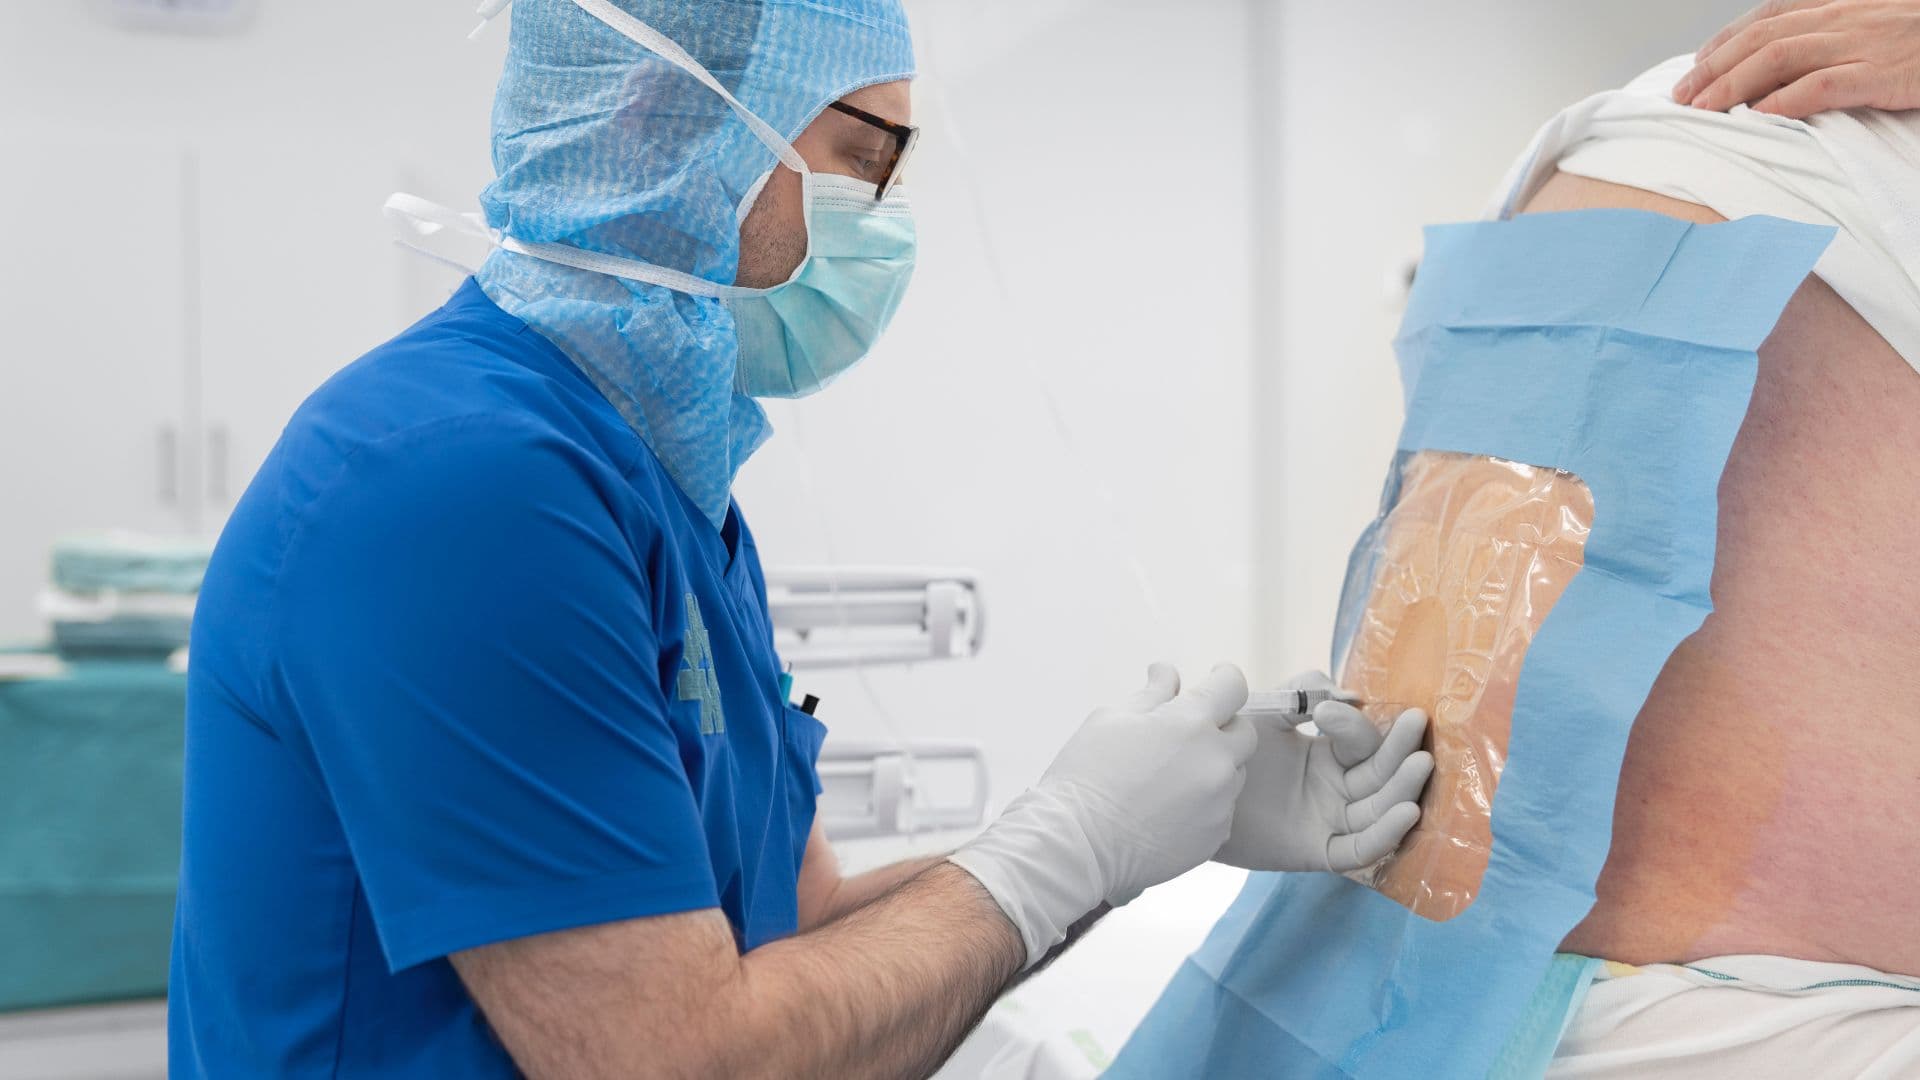
Spinal injections place medicine — usually a numbing anesthetic, often with a corticosteroid — exactly where back or neck pain starts, using live X-ray to guide the needle. They have two jobs: to show which structure is causing your pain, and to calm it enough that you can move more comfortably and get more out of physical therapy. Injections by themselves are not likely to provide long-term relief, so they work best as part of an active plan[9].
The right injection depends mostly on your pain pattern. Pain that shoots down a leg or arm, often with tingling or numbness, usually comes from an irritated nerve root and points toward an epidural steroid injection[1]. An ache that stays in the back or neck and worsens when you lean back or twist often comes from the facet joints, which are tested with a medial branch block or a facet joint injection[2]. Pain low in the back, below the belt line and into the buttock may come from the sacroiliac joint, which is tested with an SI joint injection[3].
If an injection helps but the relief wears off, the small nerves that carry pain from the facet or SI joints can sometimes be treated with radiofrequency ablation for longer relief. Our board-certified physicians perform these procedures in our office in Gramercy / Kips Bay on East 23rd Street or at an affiliated ambulatory surgery center, and recommend an injection only after reviewing your history, exam and imaging.
Epidural injections
Epidural Steroid Injections
Steroid medicine placed around irritated spinal nerves to ease sciatica, arm pain and pain from spinal stenosis.
Epidural Steroid Injections
Lumbar transforaminal epidural steroid injection
Targets a single irritated nerve root in the lower back from the side — a common choice for one-sided sciatica.
Epidural Steroid Injections
Cervical and thoracic epidural steroid injections
Epidural injections in the neck and mid-back for arm or chest-wall pain from a pinched nerve.
Facet joint treatments
Sacroiliac joint
If injections help but don’t last
Diagnostic
Conditions
Conditions we treat with spinal injections
FAQs
Spinal Injections: frequently asked questions
What is the difference between epidural, facet and SI joint injections?
They treat different pain sources. An epidural steroid injection places medicine around irritated spinal nerves and is used for pain that travels into a leg or arm[1]. A facet joint injection or medial branch block targets the small joints at the back of the spine, a common source of aching back or neck pain[2]. An SI joint injection targets the joint between the spine and pelvis, for pain low in the back and buttock[3].
How do I know which spinal injection is right for me?
Your physician decides based on where your pain is, what makes it worse, your exam and your imaging. Leg or arm pain with numbness or tingling points to a nerve root; pain that stays in the back or neck and worsens with leaning back or twisting points to the facet joints; one-sided pain below the belt line points to the SI joint. Sometimes more than one source is involved, and a diagnostic block is the clearest way to tell.
Are spinal injections painful?
Most people find spinal injections uncomfortable rather than painful. The skin is numbed first, thin needles are used and live X-ray guides placement, so most procedures take 15 to 30 minutes. You may feel pressure or a brief echo of your usual pain as the medicine goes in. Most people need little or no sedation, and some soreness at the injection site for a day or two is common.
How long do spinal injections last?
It depends on the injection and the person. Diagnostic blocks are meant to work only for hours, while the numbing medicine is active. Steroid injections may help for longer, but research shows the clearest benefit in the short term — for epidural injections, mostly within the first three months[4]. Because injections by themselves are not likely to provide long-term relief, they work best alongside exercise and physical therapy[9].
How many spinal injections can I have in a year?
Guidelines limit steroid injections to a few per year in each region of the spine and allow repeats only when the last injection clearly helped. For example, Medicare’s policy for New York allows up to four epidural sessions per spinal region in a rolling 12 months, and each repeat requires at least 50% improvement lasting three months or more[6]. Your physician will weigh the benefit against the cumulative effects of steroids.
Are spinal injections safe?
Serious complications are rare when injections are done with image guidance by experienced physicians, but no procedure is risk-free. Common effects include soreness, a short pain flare, light-headedness and a brief rise in blood sugar[9]. The FDA has not approved corticosteroids for epidural use and requires a label warning about rare but serious neurologic events after epidural injection[5]. Your physician will explain the specific risks of the injection recommended for you.
Does insurance cover spinal injections?
Medicare and most commercial plans cover epidural, facet and SI joint injections when coverage criteria are met, such as a documented trial of conservative care and image guidance[6][7][8]. Commercial plans often require prior authorization. New York workers’ compensation follows the Board’s Medical Treatment Guidelines[9], and no-fault claims have their own rules. We accept many plans, including Medicare, workers’ compensation and no-fault, and verify your benefits before scheduling.
What if spinal injections don’t help?
A lack of relief is useful information: it suggests the injected structure may not be your main pain source, and your physician may test another one. If injections help but wear off, spinal radiofrequency ablation or SI joint radiofrequency ablation may give longer relief. Other options include spinal cord stimulation and minimally invasive spine procedures, alongside continued physical therapy.
Sources
Last updated November 3, 2026. This page is educational and does not replace a consultation with your physician.
- 1.Lumbar Epidural Steroid Injection — StatPearls, NCBI Bookshelf, 2026 · Medical reference
- 2.Facet Joint Injection — StatPearls, NCBI Bookshelf, 2023 · Medical reference
- 3.Sacroiliac Joint Injection — StatPearls, NCBI Bookshelf, 2026 · Medical reference
- 4.Epidural Steroids for Cervical and Lumbar Radicular Pain and Spinal Stenosis Systematic Review Summary — Neurology — American Academy of Neurology Guidelines Subcommittee, 2025 · Review
- 5.Kenalog-40 (triamcinolone acetonide injectable suspension) prescribing information — Warnings: Serious Neurologic Adverse Reactions with Epidural Administration — U.S. Food and Drug Administration (Drugs@FDA), 2014 · Regulatory
- 6.LCD L39036: Epidural Steroid Injections for Pain Management — Centers for Medicare & Medicaid Services / Wellpoint Federal (formerly National Government Services) · Regulatory
- 7.LCD L35936: Facet Joint Interventions for Pain Management — Centers for Medicare & Medicaid Services / Wellpoint Federal (formerly National Government Services) · Regulatory
- 8.LCD L39455: Sacroiliac Joint Injections and Procedures — Centers for Medicare & Medicaid Services / Wellpoint Federal (formerly National Government Services) · Regulatory
- 9.Mid and Low Back Injury Medical Treatment Guidelines — New York State Workers’ Compensation Board, 2022 · Regulatory
Not sure which treatment is right for you?
Start with a consultation. We will find the source of your pain and recommend the least invasive option likely to help.